The Doctor on the Other End of the Line: How Health Insurers Decide What Care Gets Covered
October 16, 2026
I grew up in Korea, where nearly everyone is covered by one national health insurer run by the government. Every clinic and hospital is automatically part of its network, and most prices come from a single national fee schedule.
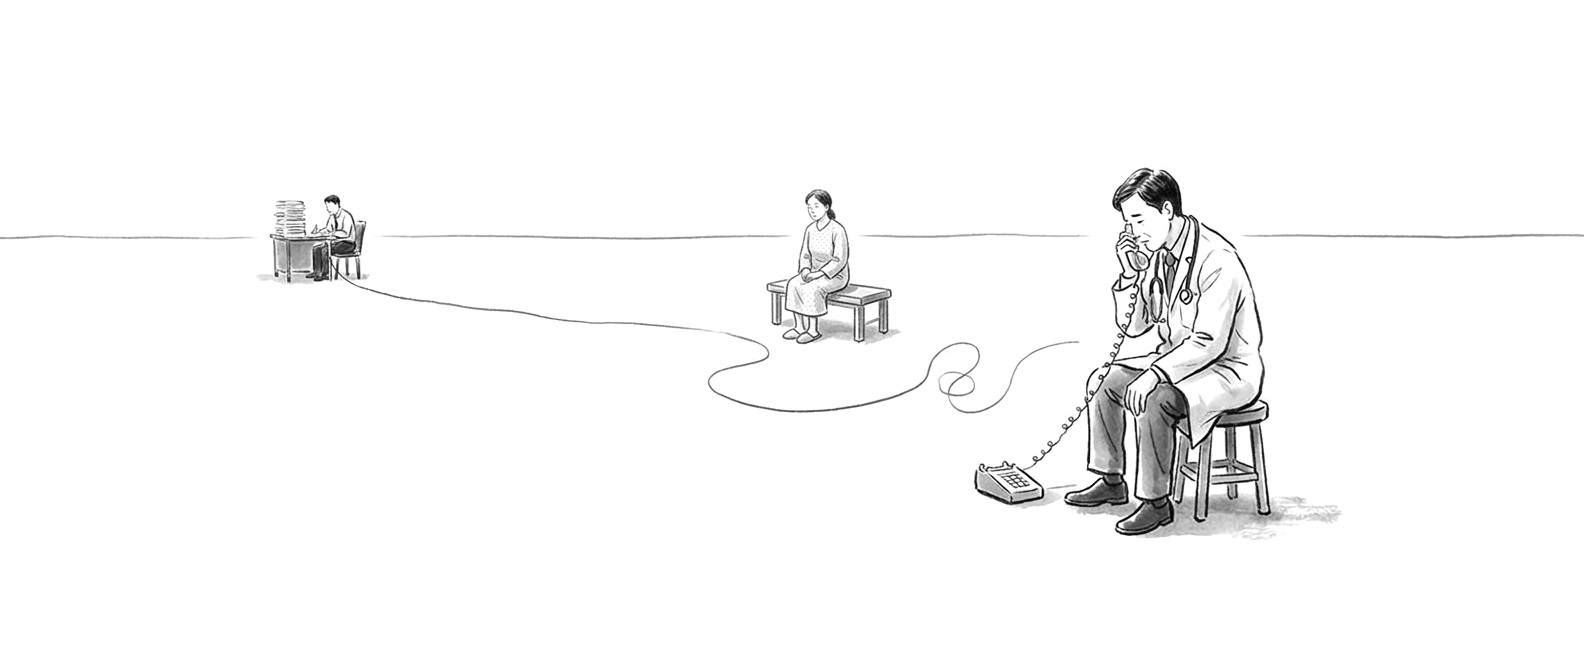
The US works nothing like that. When I started studying American healthcare this summer, I couldn't make sense of its problems until I understood who paid whom, and for what. So I drew a map. Then I followed one arrow on it, the paperwork running between insurers and doctors, down to a single phone call: the peer-to-peer review, where a treating physician tries to convince an insurer to approve a patient's care.
What interested me was how much could hinge on that conversation. I wanted to understand how it works, why doctors bear so much of the burden of challenging denials, and what might change that.
How the US healthcare system works
At the top is the government: the Centers for Medicare & Medicaid Services (CMS), state regulators, and Congress. The government funds Medicare and Medicaid, sets reference prices that much of the industry negotiates against, and regulates the participants below it.
Employers sponsor coverage for most working-age Americans. Many large employers pay their employees’ claims themselves and hire an insurer only to administer the plan. Private insurers such as UnitedHealthcare, Cigna, and the Blue Cross Blue Shield companies, alongside the public Medicare and Medicaid programs, finance care. Providers, from hospital systems to physician groups to pharmacies, deliver it.
Patients sit at the bottom of the map. Even their name depends on who's talking: a member to an insurer, a patient to a doctor, a beneficiary to Medicare.
Two things stood out once I had drawn everything out:
- The organization paying for care and the one delivering it are usually different entities, connected by contracts negotiated one relationship at a time. In Korea, many of those terms are set nationally.
- Those relationships generate an enormous amount of administrative work. Claims, prior-authorization requests, appeals, and medical records travel between organizations. Approvals, denials, payment codes, and audits come back.
The panel on the right shows what this means for a medical practice. Alongside doctors and nurses is an administrative staff of schedulers, coders, billers, and specialists who handle prior authorizations and denials. Their job is to manage the paperwork connecting the practice to the rest of the system.
I wanted to understand one part of that work in particular: what happens when an insurer says no.
How doctors challenge insurance denials
Prior authorization requires an insurer to approve certain care before it happens: an MRI, surgery, a course of radiation, or a specialty drug. Insurers argue that the process filters out unnecessary or low-value care.
Most requests are approved automatically or by a nurse checking them against established clinical criteria, such as InterQual or MCG.
A nurse can approve a request but generally cannot issue a clinical denial. Accreditation standards, Medicare Advantage rules, and many state laws require such denials to come from a physician or another qualified clinician. In practice, that person is usually a physician working for the insurer, known as a medical director.
Large insurers keep in-house benches of medical directors who review cases across many specialties. When they lack the appropriate expertise or capacity, they can bring in physicians from outside review firms, often paid per case. Since 2024, Medicare Advantage rules have also required reviewers to have expertise appropriate to the service in question, though not necessarily the same specialty as the treating doctor.
A peer-to-peer review (or P2P) gives the treating doctor an opportunity to challenge a denial directly with a physician working for the insurer. Before resorting to a formal written appeal, the treating doctor can explain the patient’s circumstances and make the case for approving the treatment.
There is no single federal process governing every P2P call, so insurers handle them differently. Some reviewers can reverse a denial during the conversation. Others can explain the decision but require a written appeal to overturn it.
The mechanics can be unforgiving. The window to request a call is often short, the conversation might last ten minutes, and arranging it can involve phone tag and long holds. If the call doesn't happen in time, the denial generally stands.
The process is supposed to put two medical professionals in conversation. Physicians say that often isn’t what happens.
In the American Medical Association’s (AMA) latest survey of 1,000 physicians, only 16% of those who had participated in P2Ps said the insurer's reviewer often or always had the appropriate qualifications. A study at one orthopedic clinic examined insurer denials of CT and MRI scans. Every reviewer was a physician, but none whose specialty could be identified was an orthopedic surgeon. Nearly all the denials were eventually approved.
The problem, then, isn’t simply that doctors have to make phone calls. It’s whether the right people are making the decisions, and whether the process gives treating physicians a meaningful chance to challenge them.
How often insurance denials delay or prevent care
Medical practices complete about 40 prior authorizations per physician each week, consuming around 13 hours of physician and staff time. Two in five physicians employ staff who work exclusively on prior authorization.
The volume is enormous. Medicare Advantage insurers alone made 52.8 million prior-authorization decisions in 2024 and denied 4.1 million of them, or 7.7%.
The consequences can extend beyond administrative inconvenience. In the AMA survey, 95% of physicians said prior authorization delays access to necessary care, about 26% said it had caused a serious adverse event for a patient, and 79% said patients abandon treatment because of it.
These are physicians' own accounts, collected by an organization that lobbies on the issue. So treat them as a signal of the scale of the problem rather than a precise measurement of its effects.
The evidence that stayed with me most, however, concerned the accuracy of the decisions themselves.
In a 2022 report, the Department of Health and Human Services’ Office of Inspector General examined a random sample of prior-authorization denials issued during one week of June 2019 by 15 of the largest Medicare Advantage insurers. It found that 13% of the denials involved care that met Medicare's coverage rules and likely would have been approved under traditional Medicare.
The main reasons were insurers applying clinical criteria stricter than Medicare's, and claiming documentation was insufficient when the medical records actually supported the requests.
Then there's what happens when doctors challenge denials.
Only 11.5% of Medicare Advantage denials were appealed in 2024, but 80.7% of those appeals were partly or fully overturned.
Two caveats matter here. These are formal appeals, not P2P calls. And the cases that get appealed are probably the strongest ones, meaning the overturn rate likely overstates how often denials are wrong.
Still, the pattern is striking. Of every 100 denials, only about 11 were formally appealed and roughly 9 of those appeals resulted in a partial or complete reversal. About 89 denials were never formally appealed at all.
Some may have been resolved through a P2P call or a resubmission, which these figures don’t capture. Others simply went unchallenged.
Why don’t more doctors contest denials? In the AMA survey, 67% said past experience led them to believe an appeal wouldn't succeed, while 55% said they lacked the time or staff.
Both answers point to the same underlying problem: challenging a denial takes work, and much of that work falls on the provider. When the cost of fighting a decision is high enough, some decisions stand not because they’ve been vindicated, but because nobody has the resources to challenge them.
Where the review process breaks down
To understand where the process fails, I mapped the P2P workflow from the moment a case approaches denial through the final documentation of the outcome.
The early steps are relatively well covered by technology. Insurer-side platforms such as Cohere Health and EviCore can approve routine requests automatically and route the rest to a human. Self-scheduling tools and voice agents that wait on hold for medical practices address the logistical burden of arranging calls. Reviewer assistants summarize case files and surface relevant clinical criteria. At the end of the process, software can draft denial letters and log the outcome.
The gaps appear closer to the actual decision.
In the products I examined, I found little direct support for the conversation itself. The closest solutions work from the case file rather than what’s said during the call, and I found little evidence that conversations are consistently captured in a structured format.
The outcome can also be difficult to act on immediately. A reviewer may explain a decision without being able to reverse it during the call. I also couldn’t find a system that systematically tells an individual reviewer when one of their decisions is later overturned.
Across the workflow, technology has focused on logistics: arranging calls, assembling records, and clearing straightforward cases. Much less appears to address the quality of the judgment at the moment it’s made.
That’s an important distinction. Making the process faster is not the same as making the decision more accurate. Better records and more efficient workflows may help, but they don’t necessarily resolve a disagreement about whether a patient should receive treatment.
And that raises a more difficult question: why, then, has more attention gone toward streamlining the process than improving the decision itself?
Why the incentives favor speed over accuracy
Start with who controls the call.
The insurer assigns the reviewer, sets the criteria, and controls the timing. Both sides spend time on P2Ps, but the cost of a call that never happens falls largely on the provider. If the doctor can’t get through in time, the denial generally stands. The insurer bears relatively little direct cost from that failed interaction.
The same imbalance appears in how insurers invest in technology.
Tools on the insurer’s side are often marketed around automation and lower medical spending. Cohere Health, one of the better-known companies in the space, highlights an 85% real-time approval rate and 15% medical-expense savings. Those are reasonable outcomes for an insurer to pursue. But they also suggest that the most immediate commercial opportunity lies in processing requests more efficiently and reducing spending; not necessarily in investing more time and resources into making every disputed decision as accurate as possible.
Hospitals face a different set of incentives. They’re often the ones absorbing the cost of bad reviews, so larger systems have spent years investing in ways to challenge denials.
Many employ physician advisors: doctors who specialize in insurance review and take P2P calls so treating physicians don’t have to step away from their patients. An established market of outsourced physician-advisory and denials firms provides similar support. Xsolis, for example, sells software that prepares cases for hospital staff before a P2P call.
Much of this market focuses on hospital stays, rather than the outpatient scans, procedures, and drugs that account for much of prior authorization.
The part that surprised me most was specialty matching.
If the core complaint is that the reviewer isn’t a peer, the obvious solution is to find one who is. But that capability already exists.
Independent review organizations (IROs) have long offered physician reviews using panels of board-certified doctors, including specialists matched to the case. Cohere says that, for plans that use its service for P2Ps, all reviews are conducted by physicians in the same specialty. A 2021 Texas law also requires the P2P reviewer to be a Texas-licensed physician in the same or similar specialty.
So the matching isn't missing. It's optional.
A small bench of generalist medical directors can process a large volume of cases quickly. Specialists, by contrast, may cost more and take longer to schedule.
I can’t demonstrate that insurers deliberately prefer mismatched reviewers, and I’d be wary of anyone who claims to know. But I found little evidence that the system consistently rewards insurers for spending more to match each case with the right expertise. Where speed is measured, the pressure can run in the opposite direction.
A 2023 ProPublica investigation offers a related, though not directly comparable, example. It reported that Cigna medical directors had denied more than 300,000 payment requests over two months using an automated system, spending an average of 1.2 seconds on each. These were payment claims, not prior authorizations, and Cigna disputed the characterization. The example doesn’t establish how P2P decisions are made, but it illustrates the broader pressure to process large volumes of healthcare decisions quickly.
The underlying problem is a gap between who controls the process and who bears the cost when it goes wrong.
Doctors and patients can suffer the consequences of a poor review. The insurer controls the process and chooses the tools used to run it, but may bear relatively little of the immediate cost when a review fails.
That gap helps explain why the system can remain inefficient even when the technology to improve parts of it already exists.
What is changing in insurance decision-making
Several developments over the past two years point toward making insurers’ decisions faster, more visible, and harder to delegate entirely to software.
Insurers must report more data on denials
Under a CMS rule finalized in 2024, Medicare Advantage, Medicaid and the Children’s Health Insurance Program (CHIP) have been subject to shorter decision deadlines since January 2026: 72 hours for urgent requests and seven days for standard requests.
The rule also requires these plans and insurers on the federal health insurance marketplace to provide specific reasons for most non-drug denials and publish prior-authorization metrics annually. The first reports were due March 31, 2026.
KFF’s analysis of 14 insurers’ 2025 data found that 12% of standard requests were denied in Medicare Advantage, 14% in Medicaid managed care, and 18% in the Affordable Care Act marketplace. Of appealed denials, 67%, 47%, and 43%, respectively, were overturned.
The differences between companies were substantial. Among the Medicare Advantage insurers in KFF’s data, denial rates ranged from 5% at Elevance to 17% at UnitedHealth Group. Overturn rates ranged from 40% at Kaiser Permanente to more than 90% at Centene.
KFF also highlighted significant limitations in the new reporting: the metrics are averaged across services, expressed as percentages without underlying counts, presented inconsistently, and often difficult to find on insurers’ websites.
It’s an imperfect start. But for the first time, the data gives employers, providers, regulators, and researchers a way to compare insurers across three insurance markets and ask why their decisions differ.
Transparency doesn’t guarantee better decisions. It does, however, make those differences harder to ignore.
Insurers pledge to reduce prior authorization
In June 2025, health insurers pledged through their trade groups to cut back prior authorization. In April 2026, AHIP, the insurers' main trade group, and the Blue Cross Blue Shield Association reported that 11% of prior authorizations had been eliminated (about 6.5 million fewer requests) with a 15% reduction in Medicare Advantage. Physicians remain skeptical: only 33% believe the pledge will make a meaningful difference.
The numbers suggest progress in reducing administrative burden, but they don’t establish whether the remaining decisions are more accurate or whether patients are receiving appropriate care more reliably.
Medicare is introducing AI-assisted prior authorization
In January 2026, CMS began the WISeR model, bringing AI-assisted prior authorization into traditional Medicare in six states through 2031, for services like spinal decompression, cervical fusion and steroid injections. A human clinician must review every denial, and providers can request peer review. However, the contractors running the program are paid a percentage of the dollar value of the requests they deny. Members of Congress have raised concerns about the model, and legislation has been introduced to block it.
The design illustrates a tension at the center of healthcare automation: software may make decisions faster, but the incentives governing how those decisions are made still matter.
Rules tighten requirements for reviewers
California's SB 1120, which took effect in January 2025, requires a licensed physician or qualified healthcare provider with relevant expertise to make medical-necessity denials. Medicare Advantage has also introduced expertise requirements, while Texas requires P2P reviewers to be physicians in the same or similar specialty.
Insurers are also facing legal scrutiny. UnitedHealth has faced a class-action lawsuit alleging that AI was used to terminate post-acute care for Medicare Advantage patients.
These developments don’t establish that every insurer is improving its decisions. They do show that the qualifications of reviewers and the role of automation are receiving greater regulatory and legal attention.
Where I believe this is heading
Three developments seem likely to me.
First, human review will remain important even as more routine decisions are automated.
In the programs and rules I examined, the trend is toward keeping qualified clinicians involved in denials while allowing software to handle more routine approvals. At least for now, automation is advancing faster on the yes than on the no.
Second, the cases reaching human reviewers will become harder.
As automation clears more straightforward requests, the remaining cases will be a smaller and more complicated group. They’ll be the cases where the clinical evidence is ambiguous, the circumstances are unusual, or the costs are high.
Those are precisely the cases in which specialist knowledge matters most.
If this prediction is right, the qualification gap identified in the AMA survey could become more consequential over time. The need for appropriate expertise won’t disappear as the volume of human reviews declines. It may become more important.
Third, accuracy will become easier to compare, even if it’s still difficult to measure.
The new reporting requirements are an imperfect start. But they give employers, providers, regulators, and researchers more information about how insurers handle prior authorization.
An insurer whose denials are overturned far more often than its competitors’ now has a published number attached to that difference. And more denials must provide a specific explanation of the decision.
I’d expect this to create gradual pressure on insurers to make decisions that are not only fast, but also accurate and defensible. That means giving reviewers the relevant criteria, the evidence supporting and challenging a request, and the full clinical record before they decide.
There are still important questions I couldn’t answer from public data.
I don’t know whether publishing these metrics will change insurer behavior when no financial penalty is attached. I couldn’t find evidence that more accurate initial reviews reduce an insurer’s total costs, which would give it a direct financial reason to invest in better decisions rather than relying on reputational pressure alone.
And I don’t know how many denials that go unchallenged reflect genuine clinical disagreements, and how many reflect doctors who simply ran out of time or resources.
Those are questions for people working inside insurers and hospitals.
When I started, I thought the problem with the P2P call was logistics: the holds, the phone tag, the missed windows. Those problems are real. But the more I learned, the more the issue seemed to be about something harder to fix: who controls the process, and who bears the cost when it goes wrong.
Technology can make the process more efficient. Making the decisions better requires something more: the right expertise, the right information, and incentives that reward getting the decision right.